General Information About Myomas
Myomas, or fibroids, are the most common tumors of the uterus. Nearly half of women of reproductive age receive a diagnosis of myoma at some point. More than ninety-nine percent of myomas do not contain malignant, or cancer, cells. Very rarely, masses thought to be myomas on ultrasound or other imaging methods may contain malignant cells.
What symptoms can myomas cause?
Myomas cause symptoms according to their location in the uterus and their size. Very small myomas in the uterine wall or growing outward may cause no symptoms. However, myomas growing toward the inside of the uterus may cause irregular bleeding or problems with becoming pregnant or continuing a pregnancy; myomas located where the tubes open into the uterus and that distort the anatomy may cause infertility. Larger myomas that enlarge the uterus overall may cause groin pain, pain during sexual activity, frequent urination, constipation and difficulty passing stool; those that grow to advanced sizes may even cause reduced exercise capacity, easy fatigue, and weakness.
What should be considered in the treatment of myomas?
Not all diagnosed myomas require treatment. For small myomas that cause no symptoms, observation alone may be sufficient. However, myomas that are large and cause the problems mentioned above require treatment.
The first step in myoma treatment is deciding whether a myoma requires treatment. Since no medical or drug treatment can completely eliminate myomas, treatment here essentially means surgery.
Options include removing only the myomas or removing the uterus completely. Removing only the myomas may be appropriate for young patients who have not yet completed their family, while removal of the uterus may also be a reasonable approach for patients who have completed their family and are in menopause. Whether only the myomas or the uterus is removed, treatment must be individualized by considering the patient's circumstances, including psychological status.
Key points when the uterus and fertility will be preserved and a future pregnancy is planned
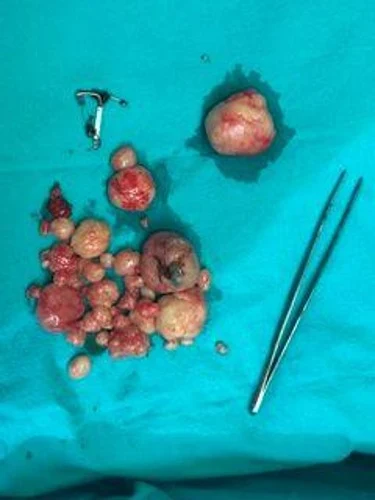
- All myomas, including millimetric ones, should be completely removed regardless of size; this can minimize the possibility of later recurrence.
- The uterine lining should not be damaged during removal. If a myoma lies close to this lining, the endometrium may be injured. Working close to the endometrium with the least adverse effect on blood supply, and repairing it properly and with the least trauma if it is damaged and the cavity is entered, will contribute positively to future pregnancy chances. Otherwise, intrauterine adhesions and difficulty conceiving may occur more often.
- If surgery is needed in the corner regions where the tubes connect to the uterus, careful incisions and sutures should aim to preserve tubal patency.
Should myomas be removed with open or laparoscopic surgery?
Myomas can be removed with both open and laparoscopic surgery. If morcellation is required to remove myomas from the body during laparoscopic surgery, case reports worldwide have described the possibility that malignant cells in a myoma could spread into the woman's abdomen (peritoneal cavity) after morcellation. This important issue must be discussed in detail with the patient before surgery. Even where there are no cancer cells, case reports indicate that myoma cells may be seeded in the abdomen during morcellation, settle there, and cause widespread myomas. This should also be discussed in detail before surgery.
The dissemination risks described above have not been reported in open myoma surgery. Therefore, when only myomas will be removed and the uterus preserved, open surgery may be considered to have an advantage in this respect.
When removal of the uterus, rather than myomas, is chosen, the surgical type may be decided according to the patient's condition, uterine size, and related factors. Return to daily life is somewhat longer after open surgery than after laparoscopic surgery. Patients almost return to daily life on the first or second postoperative day after laparoscopic surgery, whereas this period is a few days longer after open surgery.
Conclusion
When a person has myomas, the most critical step is deciding whether they should be treated or followed. Once treatment is chosen, definitive treatment is surgical removal of the myomas (myomectomy) or removal of the uterus (hysterectomy). Choosing which operation to perform is also one of the most important stages. The benefits and risks of open and laparoscopic surgery specific to myomas should be discussed sufficiently before deciding on the operation type. If removal of the myomas and preservation of the uterus are chosen, the points explained above must be carefully observed during surgery.
Whether myomas are removed or the uterus is removed, these operations can now be performed with quite low complication rates thanks to modern medicine. In addition to possible anesthesia-related complications, myoma or hysterectomy operations carry minimal risks such as bleeding, infection, injury to surrounding organs, and blood clots. If appropriate precautions are taken and these operations are performed in hospitals with suitable conditions, these risks can be managed even if they occur.
Below are the myoma nodules from a patient whose uterus we preserved and whose myomas, including millimetric ones, we removed.